PERFUSION REPORTS

REPORT
148
DATE
14/9/2026
TITLE
Consumables - cracked cardioplegia table line
DETAILS OF INCIDENT

During an elective CABG, cardioplegia was given down the root as normal with no issues. Once cardioplegia was finished the aortic root vent was turned back on under the instruction of the surgeon.

After 10 minutes of cardioplegia time, the bubble detector alarmed and it was noticed by the primary perfusionist and the n+1 perfusionist that air was being drawn up the table. The assisting perfusionist clamped the line before the air reached the surgical field and the primary perfusionist stopped the vent. The line previously was clamped before the connector. The bubble detector was put right after the luer lock connector.

‍

The surgeon was informed and the vent was turned on again after the cardioplegia line was clamped. The table line was replaced and no further issues wre noticed throughout the case in regards to cardioplegia delivery. The patient was stable and the rest of the bypass was uneventful. The patient came off bypass with no issues.

DETAILS OF INJURY TO PATIENT

The patient was extubated the day after without any post-operative complications.

‍

TYPE OF DEVICE/MANUFACTURER

Vanguard Cardioplegia Table Line. Product code REF: 075127100, LOT 2605120077. Lot/Batch No REF: 075127100, LOT 2605120077.

Date Of Manufacture 2026-05-12.  Expiry Date 2029-05-11

ACTION TAKEN

The perfusion team inspected the cardioplegia line and found that the connector was securely attached and showed no obvious signs of damage at the time of inspection. However, an evident leak was present, and it was suspected that a small fracture within the table line had allowed to open the system to air, resulting in gradual venting when the aortic root vent flow was increased. The line was clamped prior to the connector and the bubble detector was put past the connector. Therefore the alarm did notify the team at the start of the event and the team took action to resolve the issue.

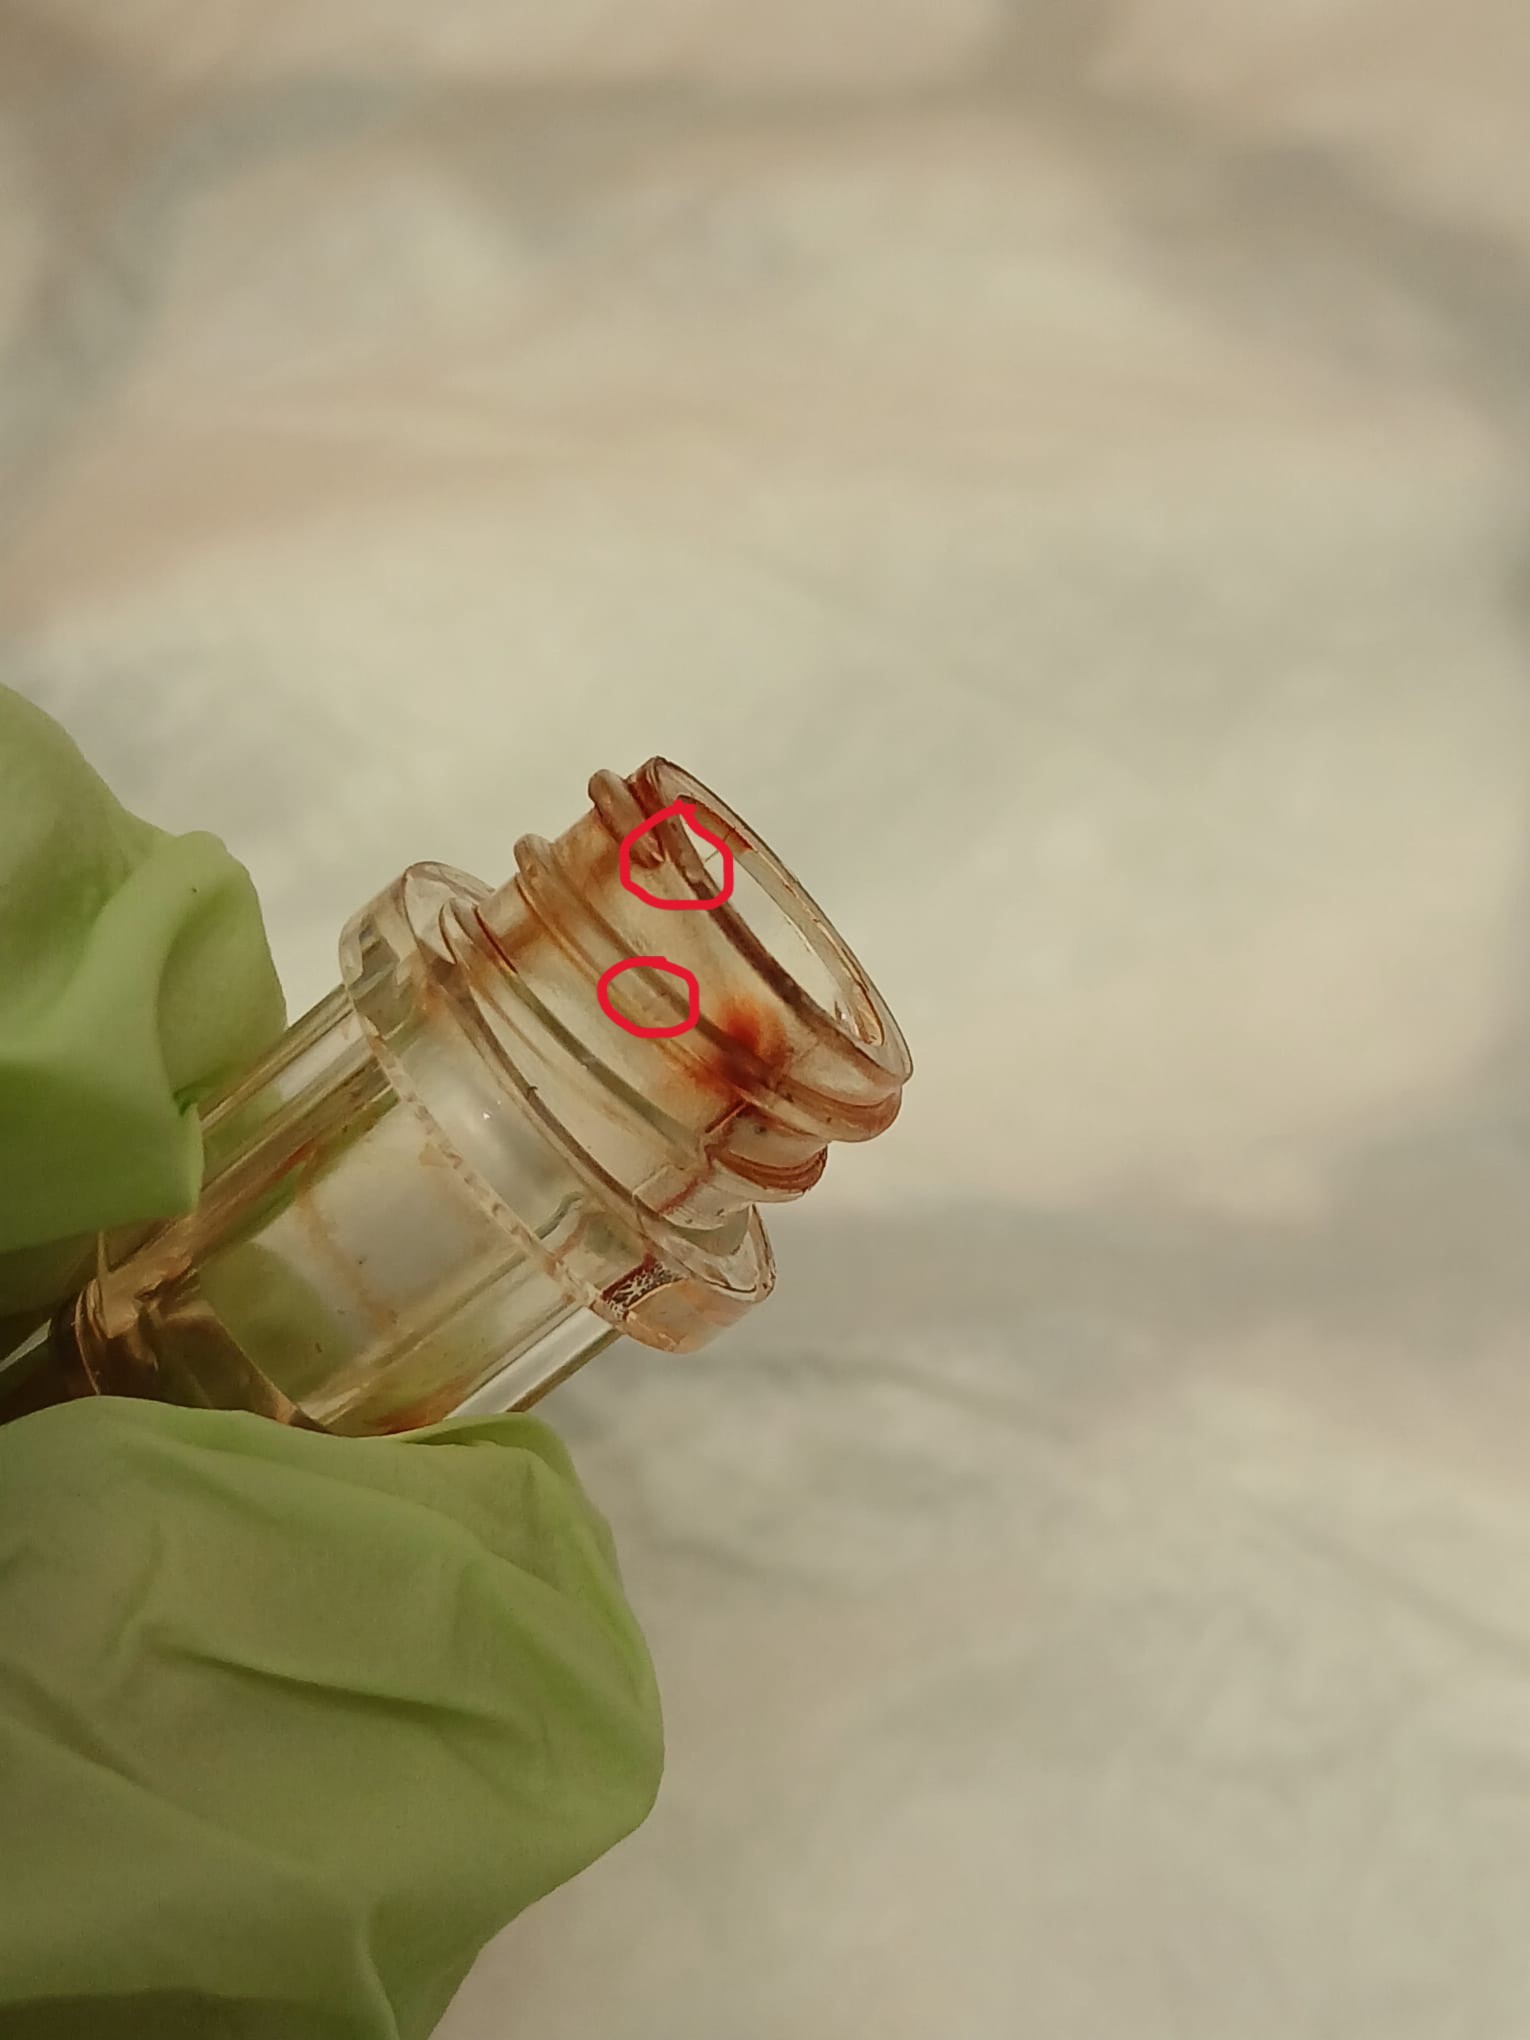
The line was retained following completion of the procedure and subsequently disinfected for further examination. On closer inspection, two small cracks were identified on the luer lock connector.

The incident has been reported to the manufacturer, and all required safety reporting processes and hospital incident reporting procedures have been completed. This was a good catch/near miss incident. The perfusion, surgical, and anaesthetic team communicated efficiently and in a calm and pragmatic approach the issue was resolved immediately with no harm done to the patient or any delays in the surgery.

RESPONSE FROM MANUFACTURER
ADDTIONAL INFORMATION
SUPPORTING VISUALS/VIDEO
SUPPORTING DOCUMENT

OTHER PERFUSION
 REPORTS

London Core Review Cardiothoracic Surgery Course - Touch icon
London Core Review Cardiothoracic Surgery Course - Help Guide
Select and scroll to view chosen report
REPORT NO
061
1/8/20
LIVA NOVA RESPONSE TO REPORTED CENTRIFUGAL HEAD ISSUE
REPORT NO
060
1/8/20
Oxygenator Fibre Leak
REPORT NO
059
1/5/20
Failure to remove CO2 effectively
REPORT NO
058
1/7/20
Centrifugal Head Issue 3
REPORT NO
057
1/6/20
Centrifugal Head Issue 2
REPORT NO
056
1/1/20
Centrifugal Head Issue
REPORT NO
055
1/2/20
Faulty Pressure Relief Valves
REPORT NO
054
1/4/20
Leaking ALF
REPORT NO
053
1/2/20
Arterial Line Filter Leak
REPORT NO
052
1/3/19
Gas Line Filter Issue
REPORT NO
051
1/12/19
Dual Lumen Cannula Movement
REPORT NO
050
1/10/19
Venous Cannula Damaged
REPORT NO
049
1/12/19
Oxygenation Issue
REPORT NO
048
1/8/19
Roller Pump Failure
REPORT NO
047
1/12/19
Broken Cannula Dilator
REPORT NO
046
6/12/19
Gas Blender Error
REPORT NO
045
20/11/19
Tubing Detachments
REPORT NO
044
27/11/19
Interruption to IABP counterpulsation
REPORT NO
043
1/7/19
Getinge Mal-Position Of IABP Catheter
REPORT NO
042
1/2/19
Avalon Dual Lumen Cannula Crack
REPORT NO
041
1/2/19
Custodial Rubber Fragmentation In Spiked Bag
REPORT NO
040
1/10/18
Reservoir Clot
REPORT NO
039
1/10/18
Pall Clot In Cardioplegia Circuit
REPORT NO
038
1/10/18
Maquet HL20 Cardioplegia Pump Error
REPORT NO
037
1/10/17
Temed D200 Haemoconcentrator Clot
REPORT NO
036
1/10/17
Oxygenator issue
REPORT NO
035
1/10/17
Medtronic Fusion Oxygenator Blood To Gas Leak
REPORT NO
034
Possible Medtronic Fusion Oxygenator Failure
REPORT NO
033
Fannin Heparin Ampules Shattering
REPORT NO
032
Sucker Placed In Raceway In Wrong Direction
Perfusion Report cards are shown in batches of 30 at any one time where available.
151
150
149
148
147
146
145
144
143
142
141
140
139
138
137
136
135
134
133
132
131
130
129
128
127
126
125
124
123
122
121
120
119
118
117
116
115
114
113
112
111
110
109
108
107
106
105
104
103
102
101
100
099
098
097
096
095
094
093
092
091
090
089
088
087
086
085
084
083
082
081
080
079
078
077
076
075
074
073
072
071
070
069
068
067
066
065
064
063
062
061
060
059
058
057
056
055
054
053
052
London Core Review Cardiothoracic Surgery Course - Touch icon
London Core Review Cardiothoracic Surgery Course - Help Guide
Know the report number? Scroll horizontally through the circle icons and select to view the appropriate report.